


Home > Blog > Hip Dysplasia: Causes, Symptoms, Diagnosis and Treatment Across the Age Spectrum (2026 Guide)
Hip Dysplasia: Causes, Symptoms, Diagnosis and Treatment Across the Age Spectrum (2026 Guide)
Filters & Insights

Medically reviewed content · Published 2026 · Last reviewed September 2026
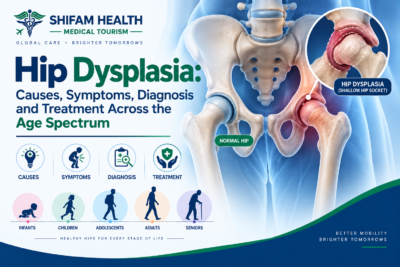
Hip dysplasia describes a hip joint where the acetabulum (hip socket) doesn’t fully or properly cover the femoral head (the ball at the top of the thigh bone), which can range from mild undercoverage causing no problems at all to significant instability or outright dislocation.
“Hip dysplasia” is not one identical condition across all ages. In babies, it’s usually called developmental dysplasia of the hip (DDH) and involves a hip that hasn’t developed normally, sometimes with actual instability or dislocation, generally detected through newborn screening. In adolescents and adults, it more often means residual or acetabular dysplasia — insufficient socket coverage that persists into or emerges in later life, causing pain, instability, or accelerated joint wear, sometimes because infant DDH was missed or incompletely corrected, and sometimes because it was never previously identified at all. These are related conditions on a spectrum, but they present, get diagnosed, and get treated in genuinely different ways depending on age, which is why this guide is organized around age rather than around a single, one-size-fits-all explanation.
This guide walks through hip dysplasia by age group — infants, toddlers and children, adolescents, and adults covering symptoms, diagnosis, and treatment options specific to each stage, along with what evaluation and treatment look like for international patients considering care in India. This is general medical education, not a diagnosis, and does not replace individualized evaluation by a qualified specialist.
Hip Anatomy and What “Dysplasia” Actually Means
The hip is a ball-and-socket joint: the femoral head (the rounded top of the thigh bone) sits within the acetabulum, a cup-shaped socket formed by the pelvis. The rim of the socket is lined by the labrum, a ring of fibrocartilage that deepens the socket and helps seal the joint, and the whole joint is enclosed by the hip capsule and surrounding ligaments. Stability and normal weight-bearing mechanics depend on the femoral head being adequately covered and centered within the acetabulum.
In dysplasia, the acetabulum is shallower or more shallow-angled than normal, providing insufficient coverage of the femoral head — this can allow excess movement or instability, place abnormal, concentrated stress on the labrum and articular cartilage at the edge of an undercovered socket, and, over years, contribute to labral injury, cartilage damage, and premature hip osteoarthritis in some patients.
Not every person with dysplasia visible on imaging has symptoms — mild or “borderline” dysplasia is common and often doesn’t cause any problems, which is why imaging findings need to be interpreted alongside symptoms and clinical examination, not treated as automatically significant on their own.
Terminology, briefly
Developmental dysplasia of the hip (DDH) is the current preferred term for what was historically called “congenital hip dislocation” — the term shifted because not every affected hip is dislocated at birth, and the condition can develop or evolve after birth, making “developmental” more accurate than “congenital.” Related terms you may encounter: hip instability (the hip moves more than it should within the socket), subluxation (partial displacement of the femoral head from the socket), dislocation (complete displacement), and, in adolescents and adults, acetabular dysplasia or residual dysplasia (persistent undercoverage), and borderline dysplasia (mild undercoverage near the threshold of what’s considered abnormal, discussed further below).
Femoroacetabular impingement (FAI) is a related but distinct hip condition — involving abnormal contact between the femur and acetabulum rather than undercoverage — that can coexist with or be confused for dysplasia and is mentioned in the differential diagnosis section below.
Causes and Risk Factors
DDH is multifactorial rather than caused by one single universal factor. Recognized associations include breech presentation (a well-established, significant risk factor), female sex (girls are affected considerably more often than boys), a family history of DDH, first-born status (thought to relate to a tighter, less-stretched uterine environment), oligohydramnios or otherwise limited intrauterine space, multiple gestation (twins or more), general “packaging” factors related to a tight intrauterine position, and, in some infants, general ligamentous laxity or connective tissue factors. DDH can also be associated with certain neuromuscular conditions or genetic syndromes, though most cases occur in otherwise healthy infants without an identifiable syndrome.
Can swaddling cause hip dysplasia?
This deserves a direct, nuanced answer: swaddling itself is not inherently harmful, but the specific position matters. Swaddling that forces the hips into extension and adduction (straight and pressed together) can interfere with healthy hip development and has been associated with increased DDH risk in some populations and historical practices.
Hip-healthy swaddling — allowing the hips and knees to bend up and out, giving the legs room to move in a natural, frog-like position, while keeping the upper body more securely wrapped — is the currently recommended approach and doesn’t carry this same concern. This isn’t about avoiding swaddling altogether or blaming parents who’ve swaddled their baby in the past; it’s about specific positioning, which many hip-healthy swaddle products and current pediatric guidance now specifically address.
Hip Dysplasia by Age: Symptoms, Diagnosis, and Treatment
Infants
Symptoms, Diagnosis & Treatment: Babies with DDH may show asymmetric skin folds, limited hip movement, leg-length difference, or hip instability, but many have no obvious signs. Diagnosis relies on physical examination, with ultrasound used in early infancy and X-rays after about 4–6 months. Treatment ranges from observation for mild immature hips to a Pavlik harness, closed or open reduction, and pelvic/femoral osteotomy for later or persistent cases. In adolescence, residual dysplasia may cause hip or groin pain and may require physical therapy or periacetabular osteotomy (PAO) for structural correction.
Adults
Adult presentations mirror the adolescent pattern — chronic groin, hip, buttock, or lateral hip pain, often activity-related, sometimes with a sense of instability, clicking, or catching — but by adulthood, a meaningful proportion of patients also have some degree of secondary osteoarthritis from years of abnormal loading, which significantly affects treatment options (discussed further below).
It’s worth emphasizing that these symptoms are not specific to dysplasia — the same symptom pattern can arise from femoroacetabular impingement, an isolated labral tear without underlying dysplasia, greater trochanteric pain syndrome, gluteal tendinopathy, or referred pain from the lumbar spine or sacroiliac joint, among other causes, which is exactly why a proper diagnostic workup (not just “hip pain, must be dysplasia”) matters.
Older adults
In older adults with longstanding dysplasia, the accumulated cartilage loss and osteoarthritis often shift the clinical picture and treatment options meaningfully — joint-preserving procedures like PAO depend on reasonably preserved cartilage to be worthwhile, and once significant arthritis has developed, the discussion generally shifts toward hip replacement rather than joint preservation, discussed below.
Red Flags: When Is Urgent Assessment Needed?
Chronic dysplasia symptoms — whether in a child with a limp or an adult with activity-related groin pain — generally warrant specialist evaluation, not emergency care. Seek prompt or urgent assessment instead for: acute, severe hip pain, especially after an injury; an inability to bear weight; suspected traumatic dislocation; fever combined with severe joint pain (a possible sign of joint infection, a genuine emergency); rapidly worsening symptoms; new numbness, tingling, or other neurovascular symptoms in the limb; or, specific to infants and young children, a child who suddenly stops walking or bearing weight on a leg, which always warrants prompt evaluation rather than a wait-and-see approach.
Imaging Tests Explained
| Test | Best Suited For | What It Shows | Key Limitation |
|---|---|---|---|
| Ultrasound | Infants, generally under 4–6 months | Cartilaginous hip anatomy, coverage, stability | Less useful once ossification progresses |
| Plain X-ray (AP Pelvis) | Older infants, children, adolescents, adults | Bony anatomy, acetabular coverage angles, joint space | Limited soft-tissue (labrum, cartilage) detail |
| False-Profile/Lateral X-ray View | Adolescents/adults | Anterior acetabular coverage specifically | Used alongside, not instead of, standard AP view |
| MRI / MR Arthrography | Adolescents/adults with suspected labral or cartilage pathology | Labrum, cartilage, soft tissue, subtle bony detail | Not typically the first test; used when a specific soft-tissue question needs answering |
| CT | Selected complex cases, surgical planning | Detailed 3D bony anatomy | Higher radiation exposure; not a routine first-line test |
Ultrasound’s importance in young infants specifically comes down to timing: before sufficient ossification develops, X-ray simply can’t show the cartilaginous hip structures ultrasound can visualize directly, which is why the two tests essentially take turns being the right tool depending on the infant’s age.
Understanding Hip Dysplasia Measurements
Clinicians use specific angle measurements to quantify dysplasia severity, but no single numerical threshold should be treated as a universal, standalone diagnosis — thresholds vary by age, skeletal maturity, imaging technique, and how the pelvis was positioned for the X-ray, and interpretation always happens alongside symptoms and clinical findings.
In infants, relevant measurements include the acetabular index (on X-ray, once applicable) and the alpha angle (on ultrasound, part of the Graf classification system used to grade infant hip maturity and stability). In adolescents and adults, the lateral center-edge angle (LCEA) is the most commonly referenced measurement, alongside the anterior center-edge angle, the Tönnis angle, and assessment of femoral version (rotation) where relevant to the overall picture.
Borderline dysplasia: a genuinely nuanced area
“Borderline dysplasia” refers to LCEA measurements that fall in a gray zone — mildly reduced coverage that doesn’t clearly meet standard thresholds for definite dysplasia but is lower than typical normal values. This is a genuinely important, often underexplained concept: a borderline measurement alone doesn’t determine whether treatment is needed — what matters more is the overall clinical picture, including whether there’s demonstrable instability, labral pathology, and how the hip actually behaves functionally, not the angle number in isolation.
This nuance is exactly why hip dysplasia diagnosis and treatment decisions, especially in adolescents and adults, benefit from a specialist experienced specifically in hip preservation, not simply a general orthopedic read of an X-ray report.
Differential Diagnosis
Conditions that can mimic or coexist with hip dysplasia include femoroacetabular impingement, an isolated labral tear, hip flexor-related pathology, greater trochanteric pain syndrome, gluteal tendinopathy, snapping hip syndrome, stress fracture, and, referred from elsewhere, lumbar spine or sacroiliac joint disorders.
In children specifically, age changes the differential substantially — Perthes disease (a childhood hip condition involving disrupted blood supply to the femoral head), slipped capital femoral epiphysis (more common in adolescents, and a condition requiring prompt evaluation given risk to the hip if missed), transient synovitis (a common, generally self-limited cause of childhood hip pain and limp), septic arthritis (a genuine emergency requiring urgent recognition), and juvenile inflammatory arthritis all need to be considered, particularly in a child presenting with new hip pain or a limp rather than known, longstanding dysplasia.
Natural History
If dysplasia is untreated or inadequately corrected, the potential progression — over years, not a fixed timeline — can include persistent instability, labral overload and injury, cartilage damage, chronic pain, activity limitation, and, in some patients, premature hip osteoarthritis eventually requiring hip replacement.
This does not mean untreated dysplasia always leads to arthritis — the natural history varies considerably between individuals, depending on the degree of undercoverage, activity level, and other factors not fully understood or predictable for any given patient. Early detection in infancy meaningfully reduces treatment complexity and generally improves the likelihood of normal hip development; for adolescents and adults with existing structural dysplasia, individualized hip-preservation assessment — not a generic assumption about inevitable arthritis — is what determines the right path forward.
Adult and Adolescent Hip-Preservation Surgery
Periacetabular osteotomy (PAO)
PAO is generally considered the gold-standard surgical treatment for symptomatic structural hip dysplasia in skeletally mature patients without significant arthritis. During PAO, the surgeon makes a series of controlled cuts around the acetabulum, allowing the socket fragment to be repositioned and reoriented to provide substantially better coverage of the femoral head, then secures it with screws while it heals into the new position. The goal is to restore more normal joint mechanics, reduce abnormal loading on the labrum and cartilage, and, for appropriately selected patients, delay or potentially avoid the eventual need for hip replacement.
Good candidacy generally requires reasonably preserved joint cartilage and hip range of motion — PAO is not intended for hips with significant existing arthritis, where the joint surface damage is already too advanced for reorientation alone to meaningfully help. Recovery involves a real period of protected or limited weight-bearing (commonly using crutches for a number of weeks), followed by progressive rehabilitation — this is a substantial surgery with a genuine recovery process, not a quick fix, and known risks include nerve injury, fracture, nonunion of the osteotomy, and the possibility that correction doesn’t fully resolve symptoms.
Modern minimally invasive PAO approaches have been associated with reduced complication rates compared to older techniques, and good long-term hip survival has been documented in appropriately selected patients, though PAO does not guarantee permanent avoidance of future arthritis or eliminate the possibility of needing further surgery.
Hip arthroscopy: what it can and can’t fix
Hip arthroscopy — a minimally invasive, camera-guided procedure — has a genuine role in treating labral tears and selected cartilage pathology. It’s essential to understand a critical limitation, though: arthroscopy alone does not correct the underlying structural undercoverage in patients whose primary problem is acetabular dysplasia. Arthroscopy addresses damage that’s already occurred (a torn labrum, damaged cartilage) but doesn’t reshape the socket itself — in a genuinely dysplastic hip, arthroscopy alone, without addressing the structural undercoverage, may provide temporary symptom relief while leaving the underlying mechanical problem, and the ongoing abnormal stress it creates, unaddressed.
This is why patient selection matters enormously: arthroscopy alone may be reasonable for a patient with normal or near-normal coverage and an isolated labral tear, while a patient with genuine structural dysplasia more often needs PAO, sometimes combined with arthroscopy to address labral or cartilage damage found at the same time, rather than arthroscopy by itself.
When is hip replacement needed?
Total hip replacement is generally a treatment for advanced arthritis and significant cartilage loss, not simply for the presence of dysplasia itself. It becomes appropriate when there’s persistent, significant pain and functional limitation from advanced joint damage, particularly after appropriate nonoperative treatment (and, where relevant, prior hip-preservation surgery) hasn’t provided adequate relief.
Dysplastic hip anatomy can add real surgical complexity to a hip replacement — abnormal bone shape and coverage can make implant positioning and achieving adequate bone support for the socket component more technically demanding than a standard replacement — which is why surgeons with specific experience in dysplastic hip anatomy are particularly valuable for this population. As with any hip replacement, risks include dislocation, infection, nerve injury, fracture, leg-length differences, and the eventual possibility of revision surgery — no responsible source should promise a specific implant lifespan or guarantee freedom from future complications.
A brief, honest note on technology
Computer-assisted planning, 3D imaging, surgical navigation, and robotic assistance are increasingly used in complex hip preservation and replacement surgery, and can improve the precision of surgical planning and execution in appropriate hands. This technology assists a surgeon’s technique — it does not, by itself, guarantee better outcomes, lower risk, faster recovery, or superior surgery, and a smaller incision or advanced navigation system is not a substitute for genuine surgeon experience with dysplastic hip anatomy specifically.
Recovery and Rehabilitation
Recovery differs substantially by treatment: an infant in a Pavlik harness needs weeks to a few months of harness wear with follow-up ultrasound, generally without a significant recovery burden for the child otherwise; a child after reduction or osteotomy typically needs a period of casting or bracing followed by gradual return to normal activity, with timelines genuinely varying by the specific procedure and the child’s age; an adolescent or adult after PAO faces a substantial recovery — commonly weeks of protected, limited weight-bearing on crutches followed by months of progressive physical therapy before full activity and sport are appropriate; and hip replacement recovery, while often allowing earlier weight-bearing than PAO, still requires structured rehabilitation over weeks to months.
No fixed universal recovery timeline applies across these very different procedures, and specific protocols vary by surgeon and institution — this is a direct conversation to have with your treating surgical team rather than something this guide can specify for your particular situation.
Exercise, Sports, and Daily Activity
Can people with hip dysplasia exercise? Generally yes — the specific answer depends on current symptoms, hip stability, cartilage condition, treatment history, and rehabilitation stage, not a blanket restriction.
Can children with treated DDH play sports? Most children treated successfully in infancy go on to participate normally in sports and activity, following their treating team’s guidance on any specific precautions.
Can adults run, cycle, swim, or squat with dysplasia? These depend heavily on individual symptoms and hip mechanics — lower-impact activities like swimming and cycling are often better tolerated than high-impact running for patients with symptomatic dysplasia, but this varies enough between individuals that generic blanket “never do X” advice isn’t appropriate; individualized guidance from a physical therapist or surgeon familiar with your specific hip is more useful than a general rule.
Can I return to competitive sports after PAO? Many patients do return to sports and higher-level activity after appropriate healing and rehabilitation, though this depends on the individual’s recovery, sport demands, and surgeon guidance — it isn’t automatic or guaranteed for every patient or every activity level.
Pregnancy and Hip Dysplasia
Pregnancy is relevant to this topic largely because PAO’s patient population skews toward women of childbearing age. Available evidence, including systematic review data, generally suggests that prior PAO does not prevent normal pregnancy or delivery for most patients, though individual circumstances (residual symptoms, specific hip mechanics, pelvic anatomy after osteotomy) can vary, and coordination between an obstetric team and the treating orthopedic surgeon can be useful for patients with more complex hip history considering pregnancy or delivery planning — this isn’t a situation with a single universal answer, and individualized discussion with both specialties is the appropriate path.
Prevention
What can realistically be influenced: hip-healthy infant positioning (avoiding tight hip extension/adduction during swaddling and babywearing), routine newborn hip screening and prompt follow-up when risk factors or exam findings suggest closer monitoring, and early treatment when DDH is identified — these genuinely reduce the likelihood of missed or late-presenting disease and its added complexity.
What cannot reliably be prevented: the underlying developmental tendency toward dysplasia itself in a given infant, which relates to genetic and in-utero factors outside anyone’s control.
Parents do not cause developmental dysplasia of the hip through ordinary infant handling or care — this bears stating plainly, since anxious parents sometimes blame themselves for a condition that’s fundamentally developmental in origin.
Long-Term Outlook
Prognosis depends on age at diagnosis, initial severity, hip stability, how promptly and effectively treatment was started, whether any residual dysplasia remains after treatment, current cartilage condition, and, for older patients, whether arthritis has already developed. Early diagnosis in infancy generally allows simpler, less invasive treatment and better long-term hip development. For adolescents and adults with structural dysplasia and preserved cartilage, hip-preservation surgery in appropriately selected patients can provide meaningful, often durable symptom relief and may delay the need for future joint replacement — though no responsible source can promise it eliminates future arthritis risk entirely or guarantees a specific long-term outcome for any individual patient.
When to See a Specialist, and Getting a Second Opinion
Seek specialist evaluation for an abnormal infant hip examination or known DDH risk factors (even without an abnormal exam), persistent limited hip motion or gait abnormality in a child, unexplained chronic groin or hip pain in an adolescent or adult (particularly activity-related), recurrent hip instability or suspected labral pathology, radiographically identified dysplasia at any age, persistent symptoms despite appropriate conservative treatment, or when PAO or another significant surgery is being considered.
A second opinion is particularly reasonable when surgery — especially PAO — has been recommended, when a child has residual dysplasia detected after prior DDH treatment, when imaging findings and reported symptoms don’t clearly align, when arthroscopy alone has been proposed for what appears to be significant structural dysplasia (given the limitation discussed above), or when there’s genuine disagreement between opinions about the right path forward.
If seeking a second opinion, gather X-rays, ultrasound reports, MRI/CT if performed, radiology reports, any prior operative notes and implant details, and your complete treatment and rehabilitation history — having the full picture available lets a second specialist give a genuinely informed opinion rather than starting from scratch.
Hip Dysplasia Treatment Cost in India
Cost depends enormously on age, whether treatment is nonoperative or surgical, and, if surgical, which specific procedure is needed.
| Component / Scenario | Approximate Cost |
|---|---|
| Pediatric orthopedic consultation | $30–$150 |
| Hip ultrasound (infant) | Modest cost, often bundled with initial evaluation |
| X-ray | $20–$80 |
| MRI / MR arthrography | $200–$600 |
| Pavlik harness treatment course (brace + follow-up) | Generally a few hundred dollars total |
| Infant/child DDH treatment overall (nonsurgical through closed reduction) | Roughly $5,000–$7,000 based on published sources, for typical cases |
| Open reduction with osteotomy (more complex pediatric cases) | Toward the higher end of, or above, the range above |
| Periacetabular osteotomy (PAO) — India-specific pricing | Not reliably established from currently available published sources; published US pricing for PAO runs roughly $15,000–$22,000+ as a general reference point for procedure complexity. This is not an India-specific figure and should not be assumed to transfer directly. |
| Total hip replacement | Follow general joint replacement pricing patterns for India, which are more extensively documented than hip-preservation-specific procedures |
Hip Dysplasia Treatment in India for International Patients
India has meaningful pediatric orthopedic and adult hip-preservation surgical capability, including centers performing PAO and complex pediatric DDH reconstruction — for international patients, the appeal is typically this capability combined with costs generally lower than the US, UK, or much of Europe.
India isn’t automatically the best or cheapest option for every patient, and this shouldn’t be assumed without direct comparison for your specific situation.
For any acute, urgent presentation — suspected traumatic dislocation, a child suddenly unable to bear weight, fever with severe joint pain — appropriate local emergency assessment should always come first, before any international travel planning.
The international patient journey
- Share medical records and existing imaging (ultrasound, X-ray, MRI/CT as applicable)
- Specialist review, appropriate to age — pediatric orthopedic or adult hip-preservation specialist
- Confirm diagnosis and discuss treatment alternatives
- Receive a treatment plan and, where possible, a cost estimate
- Arrange medical visa documentation, if travel is appropriate for the clinical situation
- Travel and attend in-person consultation, completing any needed additional investigations
- Undergo treatment if clinically appropriate
- Complete rehabilitation and receive discharge documentation
- Coordinate long-term follow-up with your home-country physician or specialist
No credible provider can guarantee surgical outcome, an exact recovery timeline, avoidance of future surgery, or an exact final cost before reviewing a patient’s actual imaging and clinical examination.
How Shifam Health Helps International Patients
Shifam Health is a medical tourism facilitator/coordinator, not a hospital, surgeon, or treating physician — we don’t diagnose hip dysplasia or determine treatment plans for you or your child.
What we do is help international patients and families navigate the practical side of accessing hip dysplasia evaluation and treatment in India: coordinating the sharing of medical records and imaging with appropriate pediatric or adult hip-preservation specialists, helping identify hospitals and surgeons with genuine relevant experience, obtaining written treatment and cost estimates, assisting with medical visa documentation, arranging airport pickup and accommodation, providing interpreter support where needed, and staying in touch for follow-up communication once you return home.
We don’t guarantee treatment success, surgical outcomes, a specific recovery timeline, or exact cost — those determinations belong to your treating medical team.
If you or your child has a suspected or confirmed hip dysplasia diagnosis and you’re exploring evaluation or treatment options in India, share your available reports and imaging with our team on WhatsApp or through a quick inquiry form — there’s no obligation, and we typically respond within 24 hours.
Frequently Asked Questions
Hip dysplasia occurs when the hip socket does not adequately cover the femoral head, potentially causing instability, pain, or early joint damage.
DDH refers to developmental hip dysplasia in infants and children, while acetabular or residual dysplasia is commonly used for adolescents and adults.
Risk factors include breech position, family history, first birth, limited space in the womb, and ligamentous laxity. It is usually multifactorial.
Possible signs include uneven skin folds, limited hip movement, or an apparent leg-length difference. However, many babies have no obvious symptoms.
Yes. Undiagnosed or residual dysplasia can cause hip or groin pain, particularly during physical activity.
Diagnosis combines physical examination with imaging. Ultrasound is preferred in young infants, while X-rays are commonly used in older children and adults.
Some immature hips stabilize naturally, but confirmed DDH requires appropriate monitoring or treatment based on severity and age.
A soft brace used mainly in young infants to keep the hips positioned correctly and encourage normal development.
Surgery may be required when bracing fails, dysplasia is diagnosed later, or significant structural abnormalities remain.
Periacetabular osteotomy (PAO) is a hip-preservation surgery that reorients the socket to improve femoral-head coverage in suitable skeletally mature patients.
Conclusion
Hip dysplasia spans a genuine range — from an infant’s hip found on newborn screening to an adult’s years-long unexplained groin pain finally explained by an X-ray measurement — and age, severity, stability, and cartilage condition together determine what a specific diagnosis means and which treatment path applies.
The most useful thing a parent or patient can do is understand which stage of this spectrum their situation falls into, since the right questions and the right specialist genuinely differ between an infant’s Pavlik harness, a teenager’s PAO decision, and an adult weighing hip preservation against eventual replacement.
If you or your child has a hip dysplasia diagnosis, finding a specialist genuinely experienced with your specific age group and severity — not simply general orthopedic care — is the most valuable step, in India or anywhere else.
This article is for general medical education and does not replace individualized assessment by a qualified pediatric orthopedic surgeon or adult hip-preservation specialist. It is not a diagnosis, treatment recommendation, or guarantee of any outcome.
Recent Posts




Quick Inquiry Form
Popular Posts From Last Week
- September 18, 2026
- shifamhealth
Written by: Shifam Health Editorial Team — Orthopedic Content Division Medically reviewed by: Shifam Health Clinical Advisory Panel…
- September 16, 2026
- shifamhealth
Ankle valgus deformity is an abnormal alignment in which the ankle tilts toward the outside of the body,…
- September 20, 2026
- shifamhealth
Medically reviewed content · Published 2026 · Last reviewed September 2026 A limb deformity in a child is…
- September 15, 2026
- shifamhealth
Medically reviewed content · Published 2026 · Last reviewed September 2026 Bow legs medically called genu varum —…
- September 15, 2026
- shifamhealth
Medically reviewed content · Published 2026 · Last reviewed August 2026 A burst fracture is a spinal vertebra…
- September 16, 2026
- shifamhealth
Epithelial ovarian cancer is the most common broad category of ovarian cancer, arising from the cells covering the…
- September 17, 2026
- shifamhealth
Hepatoblastoma is a rare malignant liver tumor that develops primarily in young children, most commonly before age 5….
- September 19, 2026
- shifamhealth
Finding a purple or reddish patch on your skin that won’t fade, or hearing “Kaposi sarcoma” mentioned during…
- September 18, 2026
- shifamhealth
Kyphosis means forward curvature of the spine — and some kyphosis is completely normal anatomy in the mid-back…
- September 21, 2026
- shifamhealth
Medically reviewed content · Published 2026 · Last reviewed September 2026 Hip dysplasia describes a hip joint where…
- September 19, 2026
- shifamhealth
Lumbar radiculopathy is a neurological syndrome caused by irritation, inflammation, or compression of a nerve root in the…
- September 20, 2026
- shifamhealth
Still having pain after spine surgery — whether it never fully went away, or came back after a…